
Stimulant Addiction: Signs, Types, and Treatment

Stimulant addiction is the compulsive use of drugs that speed up the central nervous system, and clinicians diagnose the condition as stimulant use disorder. The category covers cocaine, methamphetamine, and prescription stimulants.
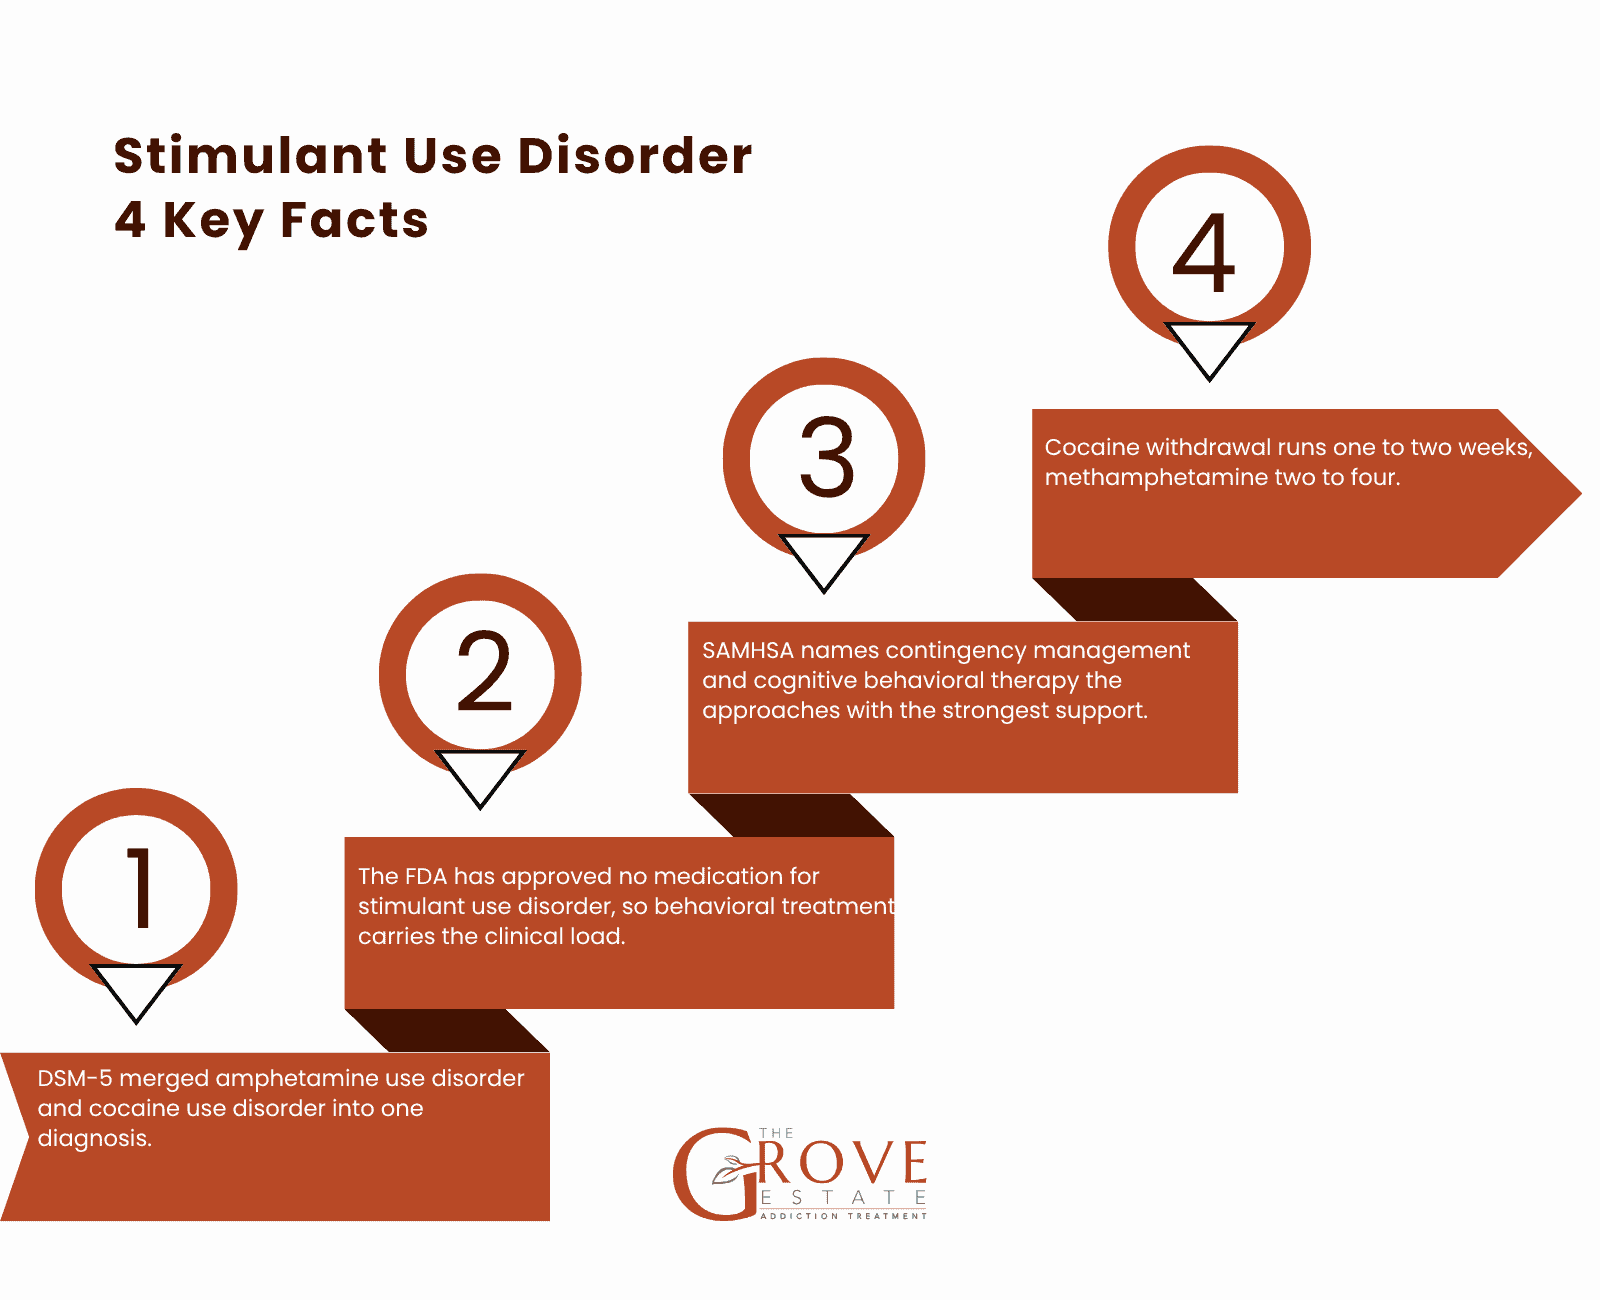
DSM-5-TR treats these substances as one diagnosis rather than several. Amphetamine use disorder and cocaine use disorder were merged because both drug groups act on the same signaling system.
No medication holds FDA approval for this condition. That single fact reshapes what treatment looks like, and it separates stimulant use disorder from opioid or alcohol use disorder.
Knowing which drugs belong in this category is where recognition starts.
Key Takeaways
- DSM-5-TR combines two former diagnoses. The American Psychiatric Association merged amphetamine use disorder and cocaine use disorder into a single stimulant use disorder diagnosis, because both drug classes produce comparable effects.
- The Substance Abuse and Mental Health Services Administration states in Treatment Improvement Protocol 33 that the Food and Drug Administration has not approved any medication for stimulant use disorders.
- Contingency management carries the strongest evidence. That same protocol identifies contingency management and cognitive behavioral therapy as the approaches holding the greatest empirical support.
- Clinicians tally how many of 11 diagnostic criteria a person meets within 12 months, which grades the disorder as mild, moderate, or severe.
- Withdrawal requires monitoring for a specific reason. SAMHSA identifies self-harm as the greatest risk during stimulant withdrawal, even though stimulant withdrawal produces no physiologic disruption that requires a gradual taper.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Is Stimulant Addiction?
Stimulant addiction is a diagnosable condition in which repeated stimulant use continues despite accumulating harm, and DSM-5-TR names that condition stimulant use disorder.
How DSM-5-TR Classifies Stimulant Use Disorder
DSM-5-TR assigns one diagnostic category to stimulants that share a mechanism, which places cocaine and amphetamine under a single label.
- One diagnosis replaced two: The American Psychiatric Association merged amphetamine use disorder and cocaine use disorder into stimulant use disorder, because amphetamines and cocaine generate similar effects.
- The specifier names the substance: A clinician records which stimulant is involved, so the diagnosis reads amphetamine-type substance, cocaine, or other stimulant.
- Severity attaches to the diagnosis itself: DSM-5-TR grades stimulant use disorder as mild, moderate, or severe according to the criteria count.
- Caffeine sits outside the category: DSM-5-TR recognizes caffeine intoxication and caffeine withdrawal but includes no caffeine use disorder, which separates caffeine from the stimulants this diagnosis covers.
What Separates Stimulants From Other Drug Classes
Stimulants accelerate central nervous system activity, which places them opposite the drug classes that suppress it.
- Direction of effect defines the class: Stimulants elevate heart rate, blood pressure, alertness, and motor activity, while depressants suppress those same systems. The contrast between stimulants and depressants explains why the two withdrawal syndromes differ so sharply.
- Legal status cuts across the class: Cocaine and methamphetamine carry no routine prescribing role, while amphetamine and methylphenidate treat attention-deficit/hyperactivity disorder under prescription.
- Tolerance develops quickly: Repeated dosing reduces the response to a given amount, and rising tolerance drives the escalation that marks the disorder.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
Which Drugs Are Stimulants?
Stimulants divide into illicit stimulants, prescription stimulants, and synthetic compounds sold outside regulated supply chains.
Illicit Stimulants
Illicit stimulants reach users through unregulated supply, which removes any control over dose or purity.
- Cocaine: A short-acting stimulant extracted from coca leaf, cocaine produces effects lasting minutes to roughly an hour, which drives repeated dosing within a single session.
- Crack cocaine: The smokable form delivers the dose to the bloodstream through the lungs, which shortens onset and intensifies the reinforcing effect.
- Methamphetamine: Methamphetamine produces a substantially longer duration of action than cocaine, which extends both the intoxication period and the withdrawal that follows.
Prescription Stimulants
Prescription stimulants treat diagnosed conditions at controlled doses, and misuse begins when dosing departs from the prescription.
- Amphetamine and dextroamphetamine: These compounds treat attention-deficit/hyperactivity disorder and narcolepsy, and misuse commonly involves higher doses or non-oral routes.
- Lisdexamfetamine: A prodrug that requires enzymatic conversion before it becomes active, Vyvanse reaches peak effect more slowly than immediate-release amphetamine.
- Methylphenidate: Methylphenidate blocks dopamine reuptake rather than forcing dopamine release, which distinguishes its mechanism from the amphetamines.
- Wakefulness-promoting agents: Compounds such as modafinil treat narcolepsy and shift work sleep disorder through a mechanism that differs from classical stimulants.
Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Synthetic Cathinones
Synthetic cathinones mimic amphetamine pharmacology while sitting outside pharmaceutical manufacturing standards.
- Composition varies between batches: Products sold as bath salts contain differing compounds at differing concentrations, which makes any given dose unpredictable.
- Agitation presents severely: Compounds such as synthetic cathinones generate severe agitation and hyperthermia that bring users to emergency departments.
What Causes Stimulant Use Disorder?
Stimulant use disorder develops through pharmacological reinforcement, inherited vulnerability, developmental exposure, and untreated psychiatric conditions acting together.
How Stimulants Act on Dopamine Signaling
Stimulants raise synaptic dopamine, and the route each drug takes to that outcome differs by compound.
- Cocaine blocks the transporter: Cocaine inhibits the dopamine transporter (DAT), which prevents reuptake and leaves dopamine in the synapse longer than normal signaling permits.
- Amphetamines force release: Amphetamines reverse vesicular monoamine transporter 2 (VMAT2) activity, which actively pushes stored dopamine into the synapse rather than merely blocking its removal.
- Norepinephrine drives the physical effects: Stimulants elevate norepinephrine alongside dopamine, which produces the tachycardia and hypertension that define sympathomimetic toxicity.
- Repeated surges reset the baseline: Sustained stimulant exposure dysregulates the brain reward system, which flattens the response to ordinary rewards.
Rediscover Life at The Grove Estate
Get the compassionate mental health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our Facility
Genetic and Family Factors
Inherited variation shapes how strongly a person responds to a first stimulant exposure.
- Family history raises risk: A parental history of substance use disorder increases risk across substance classes, including stimulants.
- Metabolism differs between people: Individual variation in drug-metabolizing enzymes changes how long a given dose remains active.
Psychiatric Conditions and Self-Medication
Untreated psychiatric symptoms create a reason to use stimulants that has nothing to do with recreation.
- Untreated ADHD precedes some misuse: Undiagnosed attention-deficit/hyperactivity disorder motivates stimulant use for concentration, which establishes a pattern before any diagnosis occurs.
- Depression interacts with the crash: Stimulants briefly lift mood, and the depressive rebound afterward reinforces further dosing to escape it.
- Co-occurring conditions require joint treatment: Co-occurring disorders persist after stimulant use stops, which is why sequential treatment produces worse results than integrated treatment.
Route of Administration
How a stimulant enters the body governs how strongly it reinforces repeat use.
- Faster onset reinforces harder: Smoking and injection deliver the dose to the brain within seconds, which strengthens the association between the act and the effect.
- Escalation follows the route: Users who move from oral to intranasal or inhaled routes raise both the intensity and the frequency of dosing.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Are the Signs of Stimulant Use Disorder?
Stimulant use disorder presents through behavioral changes, physical effects, and psychiatric symptoms that intensify as use continues.

Common Signs
Early stimulant use disorder shows in sleep, appetite, and daily functioning before medical complications appear.
- Sleep collapses: Stimulants suppress sleep drive, which produces extended waking periods followed by prolonged crash sleep.
- Appetite falls and weight drops: Stimulants suppress appetite directly, which generates weight loss that others notice before the person does.
- Spending outpaces income: Escalating doses raise cost, which produces borrowing and unexplained financial pressure.
- Talkativeness and restlessness increase: Elevated dopamine and norepinephrine produce pressured speech and an inability to sit still.
Severe Signs and Emergency Warning Signs
High-dose stimulant use produces cardiovascular and psychiatric emergencies that require immediate medical attention.
- Chest pain demands emergency care: Stimulants constrict coronary arteries and raise cardiac workload, which precipitates myocardial infarction even in young users.
- Body temperature climbs dangerously: Hyperthermia during stimulant intoxication damages organs and requires active cooling.
- Seizures occur at high doses: Stimulant overdose lowers the seizure threshold, which produces convulsions requiring emergency intervention.
- Psychosis presents with paranoia and hallucinations: Stimulant-induced psychosis generates persecutory beliefs and tactile hallucinations, including formication, the sensation of insects moving beneath the skin.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
Long-Term Effects
Sustained stimulant use produces cardiac, dental, and neurocognitive changes that persist beyond active use.
- Psychosis becomes easier to trigger: After one psychotic episode, SAMHSA reports that a lower dose induces another episode with faster onset and longer duration than the first.
- Cardiac damage accumulates: Repeated hypertensive episodes thicken cardiac muscle and scar coronary vessels.
- Cognition slows measurably: Chronic methamphetamine use impairs attention, memory, and decision-making, and recovery takes months of abstinence.
- Dental damage progresses: Reduced saliva, bruxism, and neglected hygiene during methamphetamine use combine to destroy tooth structure.
How Long Does Stimulant Withdrawal Last?
Stimulant withdrawal begins one to four days after the last dose and resolves across one to four weeks depending on the substance.
The Withdrawal Timeline
SAMHSA describes stimulant withdrawal as a phased process rather than a single event, with cocaine resolving faster than methamphetamine.
- Onset, 1 to 2 days after cocaine or 2 to 4 days after methamphetamine: Withdrawal symptoms begin once the drug clears, and the interval differs by compound.
- The crash, the first several days: This acute phase produces dysphoria, anxiety, and agitation alongside fatigue and depressed mood.
- The wall, the following days to weeks: Profound hypersomnolence, fatigue, mood lability, and increased appetite dominate this postacute phase.
- Resolution, 1 to 2 weeks for cocaine: Cocaine withdrawal persists across one to two weeks, which makes it shorter than methamphetamine withdrawal.
- Resolution, 2 to 4 weeks for methamphetamine: Methamphetamine withdrawal persists two to four weeks and becomes protracted in some cases.
- Around one month: A euphoric phase clinicians call the pink cloud appears near the one-month mark.
- Protracted phase: Fatigue, loss of physical and mental energy, depression, and anhedonia continue past the acute period.
Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Why Stimulant Withdrawal Still Requires Supervision
Stimulant withdrawal carries a different risk profile from alcohol withdrawal, and that difference determines what supervision targets.
- No taper is physiologically required: SAMHSA reports that no consistent physiologic disruptions requiring gradual withdrawal have been observed with stimulants.
- Self-harm is the primary danger: SAMHSA identifies doing harm to self as the greatest risk during stimulant withdrawal, which makes psychiatric monitoring the central safeguard.
- Depression peaks when support is thinnest: The depressive phase arrives after the acute crash, which is precisely when unsupervised individuals resume use.
- Sleep disruption compounds risk: Alternating insomnia and hypersomnolence destabilize mood during the same window. General withdrawal symptoms differ substantially between drug classes.
How Is Stimulant Use Disorder Diagnosed?
Clinicians diagnose stimulant use disorder by counting how many of 11 DSM-5-TR criteria a person meets during a 12-month period.
The Diagnostic Criteria and Severity Thresholds
DSM-5-TR groups its 11 criteria into four domains, and the total count sets the severity grade.
- Impaired control: Using larger amounts or for longer than intended, a persistent desire to cut down, spending significant time obtaining or recovering from use, and craving.
- Social impairment: Failing work, school, or home obligations, continuing use despite interpersonal problems, and abandoning recreational or occupational activities.
- Risky use: Using in physically unsafe situations, and continuing despite knowing it worsens a physical or psychological problem.
- Pharmacological criteria: Tolerance requiring higher doses, and withdrawal symptoms when levels fall.
- Severity follows the count: Two or three criteria indicate mild, four or five indicate moderate, and six or more indicate severe stimulant use disorder.
Rediscover Life at The Grove Estate
Get the compassionate mental health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our FacilityThe Named Withdrawal Severity Scale
Clinicians quantify stimulant withdrawal severity with a validated instrument rather than a subjective impression.
- The Cocaine Selective Severity Assessment (CSSA): Kampman and colleagues at the University of Pennsylvania developed this 18-item interviewer-administered scale, which rates withdrawal features including craving, lethargy, sleep change, appetite change, irritability, and paranoia. Higher total scores indicate more severe withdrawal.
- Scores predict outcomes: Kampman and colleagues reported that initial CSSA scores correlated with recent cocaine use and with Addiction Severity Index measures.
Stimulant Use Disorder vs Prescribed Stimulant Dependence
Physiological dependence on a correctly prescribed stimulant is not the same condition as stimulant use disorder, and DSM-5-TR draws that line explicitly. Where prescribed use has crossed that line, adderall addiction treatment addresses it.
| Feature | Prescribed stimulant dependence | Stimulant use disorder |
|---|---|---|
| Dosing pattern | Follows the prescription as written | Exceeds the prescription or uses non-oral routes |
| Tolerance and withdrawal | Present, but excluded from the criteria count when taken as prescribed | Counted toward the diagnosis |
| Functioning | Improves at work, school, and home | Deteriorates across those domains |
| Control over use | Intact, with no craving or failed cut-down attempts | Impaired, with craving and failed attempts to stop |
Why the Distinction Changes Clinical Decisions
Confusing dependence with a use disorder produces two opposite errors, and both cause harm.
- Overdiagnosis interrupts effective treatment: Treating a stable prescribed patient as addicted removes a medication that was improving function.
- Underdiagnosis delays care: Accepting a prescription as proof that no disorder exists misses escalation happening around the prescription.
- Route of use resolves most cases: Crushing, snorting, or injecting a prescribed stimulant departs from prescribed use regardless of the dose written.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
How Is Stimulant Use Disorder Treated?
Treatment for stimulant use disorder rests on behavioral interventions, because no medication holds FDA approval for the condition.
First-Line Behavioral Treatment
SAMHSA identifies the psychosocial and behavioral approaches that hold the strongest empirical support for stimulant use disorder.
- Contingency management: This approach delivers tangible incentives contingent on objectively verified abstinence, and SAMHSA names it among the approaches with the greatest empirical support.
- Cognitive behavioral therapy and relapse prevention: SAMHSA pairs cognitive behavioral therapy with contingency management as the other approach carrying that level of support.
- The community reinforcement approach: This method restructures the daily environment so that non-drug activities compete with stimulant use.
The Evidence Behind Contingency Management
Contingency management traces to a specific research program rather than to general behavioral theory.
- Stephen T. Higgins developed the voucher model: Higgins and colleagues at the University of Vermont established voucher-based reinforcement, in which patients earn vouchers exchangeable for retail goods contingent on drug-negative urinalysis.
- Effects persisted after treatment ended: Higgins and colleagues reported that abstinence-contingent incentives increased cocaine abstinence during outpatient treatment and across one year of follow-up.
- Federal policy now recognizes it: The Office of the Assistant Secretary for Planning and Evaluation published federal guidance on contingency management for substance use disorders in 2024.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
Why No Medication Is Approved
The absence of an approved medication for stimulant use disorder reflects a pharmacological problem rather than a lack of research effort.
- SAMHSA states the position directly: Treatment Improvement Protocol 33 explains that the Food and Drug Administration has not approved any medications for stimulant use disorders.
- No replacement agent exists: Opioid use disorder has agonist medications and alcohol use disorder has approved agents, while stimulant use disorder has no comparable substitution therapy.
- Off-label agents remain investigational: Researchers continue testing compounds for stimulant use disorder, and none has reached approval.
Level of Care and Continuing Support
Where treatment happens depends on assessed clinical need rather than on the substance alone.
- Residential care removes access: A structured residential setting interrupts the cue environment that sustains stimulant use.
- Psychiatric monitoring addresses the real risk: Supervision during the depressive withdrawal phase targets the self-harm risk SAMHSA identifies.
- Commercial and editorial paths differ: Individuals seeking care specifically for cocaine use disorder follow a different route from those researching the drug class.
- Support continues after discharge: Anhedonia persists into the protracted phase, which makes continuing care a clinical requirement rather than an optional extra.
Treatment at The Grove Estate
The Grove Estate treats stimulant use disorder within a single designated level of care on a 25 acre estate in Peru, Miami County, Indiana.
Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Licensing and Level of Care
The Grove Estate holds one designated level of care, which defines what the facility delivers.
- ASAM Level 3.5 residential: The facility operates as Clinically Managed High-Intensity Residential care for voluntary adults aged 18 and older.
- Joint Commission accreditation: The Behavioral Health Care and Human Services Accreditation Program lists the organization under Health Care Organization ID 696218.
- State designation: The Indiana Family and Social Services Administration Division of Mental Health and Addiction lists the facility as an active provider under reference number 2145-010.
- Licensed capacity: The estate operates a licensed capacity of 31 to 50 beds.
Withdrawal Management Within Residential Treatment
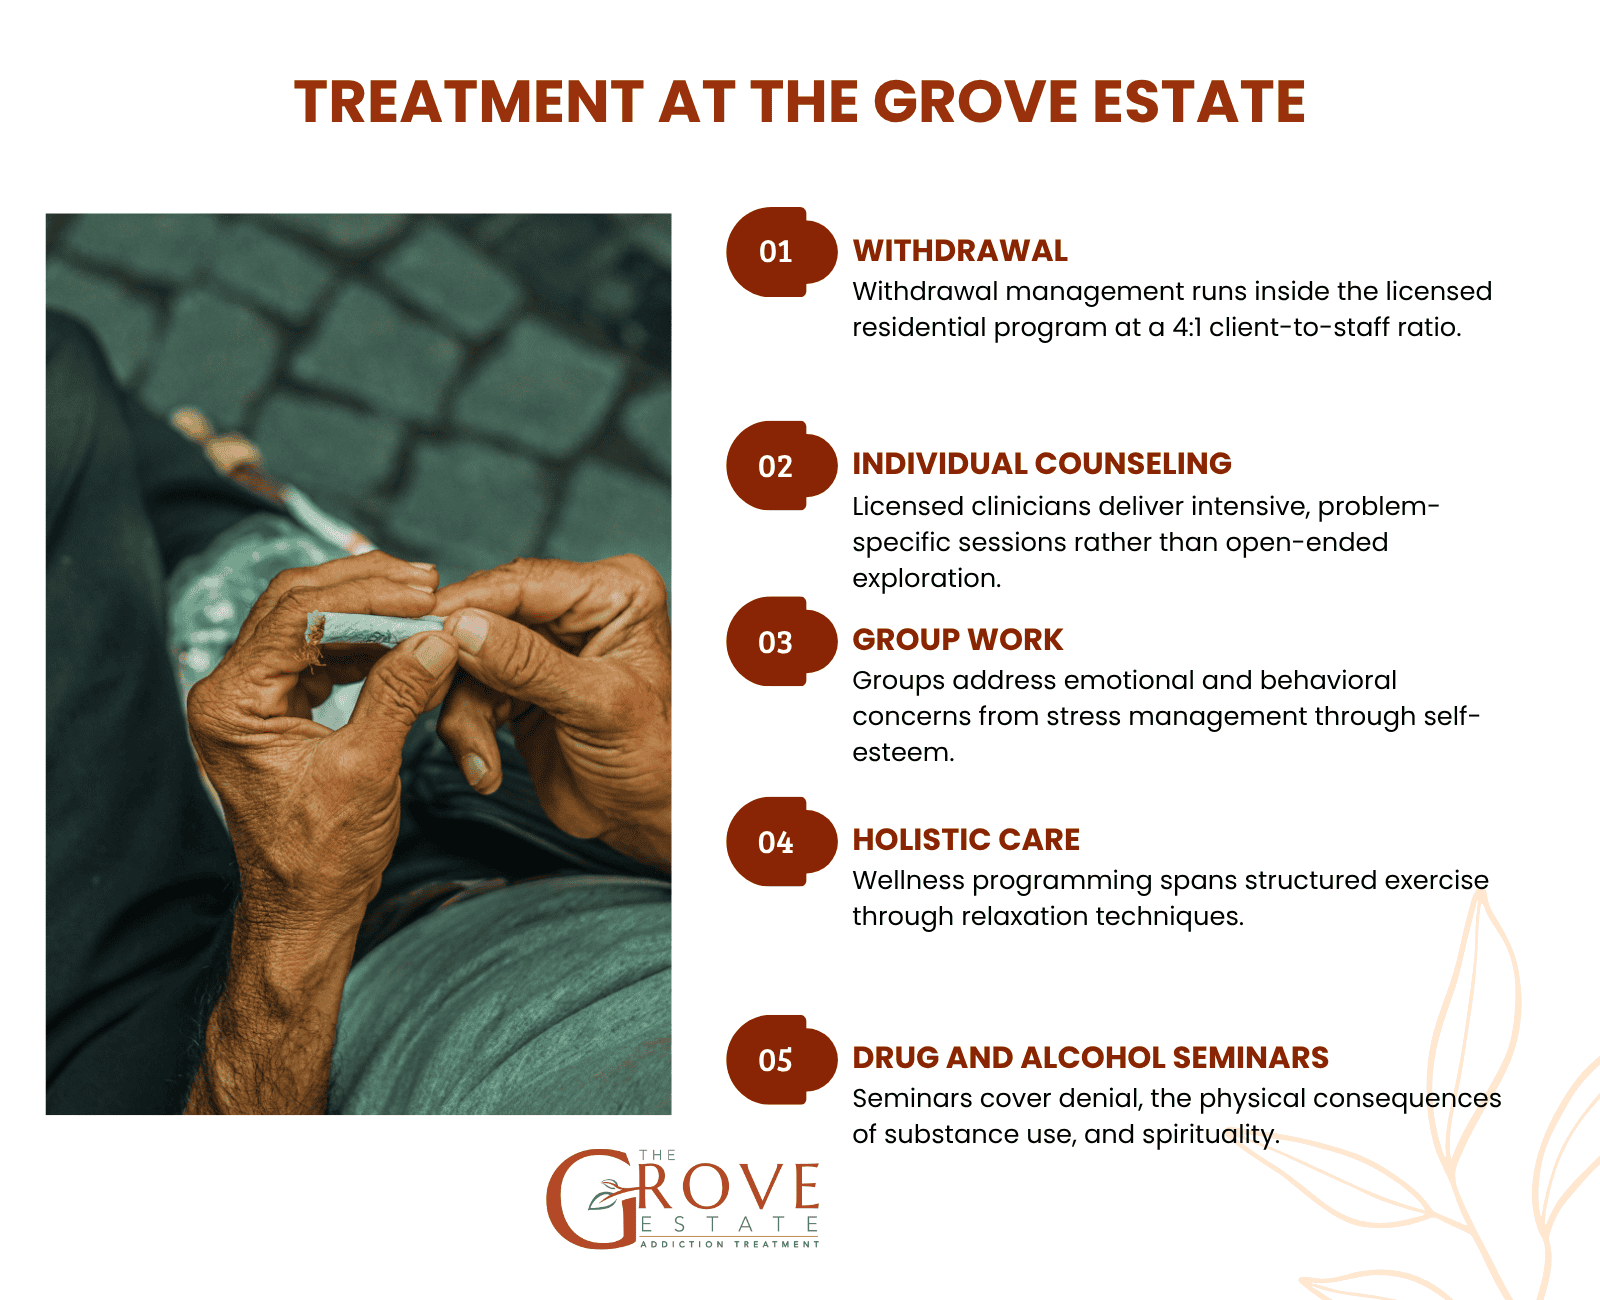
Withdrawal management within residential treatment at The Grove Estate runs inside the licensed residential program rather than as a separate unit.
- Staffing ratio: Withdrawal management operates at a 4:1 client-to-staff ratio.
- Clinical oversight: Physician-directed medication and 24-hour nursing oversight support clients through the acute phase.
- Psychiatric attention during the crash: The depressive phase of stimulant withdrawal receives monitoring because self-harm risk peaks there.
Counseling and Group Programming
Residential rehab at The Grove Estate delivers care at a 12:1 client-to-staff ratio across six programming elements.
- Individual counseling: Licensed clinicians deliver intensive, problem-specific sessions rather than open-ended exploration.
- Group counseling: Groups address emotional and behavioral concerns ranging from stress management to self-esteem.
- Alcohol and drug seminars: Seminars cover denial, physical consequences, and spirituality.
- Wellness programs: Programming spans structured exercise through relaxation techniques.
- Family program: Structured family involvement runs alongside residential care.
- Recreational therapy: Expressive and activity-based sessions form part of the residential schedule.
Rediscover Life at The Grove Estate
Get the compassionate mental health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our FacilityFrequently Asked Questions
What are the 7 common stimulant drugs?
Commonly listed stimulants include cocaine, methamphetamine, amphetamine, dextroamphetamine, methylphenidate, lisdexamfetamine, and synthetic cathinones. DSM-5-TR groups amphetamine-type substances and cocaine under one stimulant use disorder diagnosis, and it excludes caffeine from that category.
What are the symptoms of overusing stimulants?
Overuse produces sleep loss, appetite suppression, weight loss, pressured speech, and restlessness. High doses generate chest pain, hyperthermia, seizures, and psychosis with paranoia. Chest pain during stimulant use requires emergency assessment, because stimulants precipitate myocardial infarction in young users.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
Are ADHD stimulants addictive?
Prescription stimulants carry addiction potential, though taking them as prescribed for attention-deficit/hyperactivity disorder differs from stimulant use disorder. Risk rises when dosing exceeds the prescription or shifts to crushing, snorting, or injecting the medication.
Is being dependent on prescribed stimulants the same as addiction?
No. DSM-5-TR excludes tolerance and withdrawal from the criteria count when a stimulant is taken as prescribed. Stimulant use disorder requires impaired control, social impairment, or risky use, not merely a physiological response to consistent dosing.
How long does stimulant withdrawal last?
Cocaine withdrawal begins one to two days after the last dose and persists one to two weeks. Methamphetamine withdrawal begins two to four days after the last dose and persists two to four weeks, and it becomes protracted in some cases.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
Why do people use stimulants?
Motivations include alertness, concentration, appetite suppression, and euphoria. Undiagnosed attention-deficit/hyperactivity disorder motivates some stimulant use for focus, which establishes a pattern before any clinical assessment happens.
How are stimulants misused?
Misuse includes taking more than prescribed, using someone else’s prescription, and crushing tablets for snorting or injection. Faster routes deliver the dose within seconds, which strengthens reinforcement and accelerates escalation.
When should someone seek help for stimulant use?
Seek help once use continues despite harm, once cutting down fails, or once craving governs the day. The SAMHSA National Helpline provides free, confidential, 24-hour referral at 1-800-662-4357.
Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!References
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Association Publishing.
- Substance Abuse and Mental Health Services Administration. (2021). Treatment for stimulant use disorders (Treatment Improvement Protocol Series, No. 33). U.S. Department of Health and Human Services. Available at ncbi.nlm.nih.gov
- Higgins, S. T., Wong, C. J., Badger, G. J., Ogden, D. E., & Dantona, R. L. (2000). Contingent reinforcement increases cocaine abstinence during outpatient treatment and 1 year of follow-up. Journal of Consulting and Clinical Psychology, 68(1), 64-72.
- Kampman, K. M., Volpicelli, J. R., McGinnis, D. E., Alterman, A. I., Weinrieb, R. M., D’Angelo, L., & Epperson, L. E. (1998). Reliability and validity of the Cocaine Selective Severity Assessment. Addictive Behaviors, 23(4), 449-461.
- Kampman, K. M. (2008). The search for medications to treat stimulant dependence. Addiction Science & Clinical Practice, 4(2), 28-35.
- McNeely, J., Hamilton, L. K., Whitley, S. D., et al. (2024). Substance use screening, risk assessment, and use disorder diagnosis in adults. Johns Hopkins University.
- Office of the Assistant Secretary for Planning and Evaluation. (2024). Contingency management for the treatment of substance use disorders: Enhancing access, quality, and program integrity for an evidence-based intervention. U.S. Department of Health and Human Services.
- National Institute on Drug Abuse. (2018). Principles of drug addiction treatment: A research-based guide (3rd ed.). National Institutes of Health. Available at nida.nih.gov
Share This Post

The Grove Editorial Team
All author posts
ADDICTION TREATMENTS IN INDIANA
Are you covered for treatment?








The Grove Estate is an approved provider for Blue Shield of California and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!

