
Mindfulness in Recovery: Techniques and Relapse Prevention

Mindfulness in addiction recovery means training attention so that a craving can be noticed and tolerated rather than acted on automatically.
Two manualized protocols apply it specifically to substance use, and both have published trial evidence.
The techniques themselves are simple to describe and difficult to sustain, which is why the protocols are structured courses rather than advice.
Key Takeaways
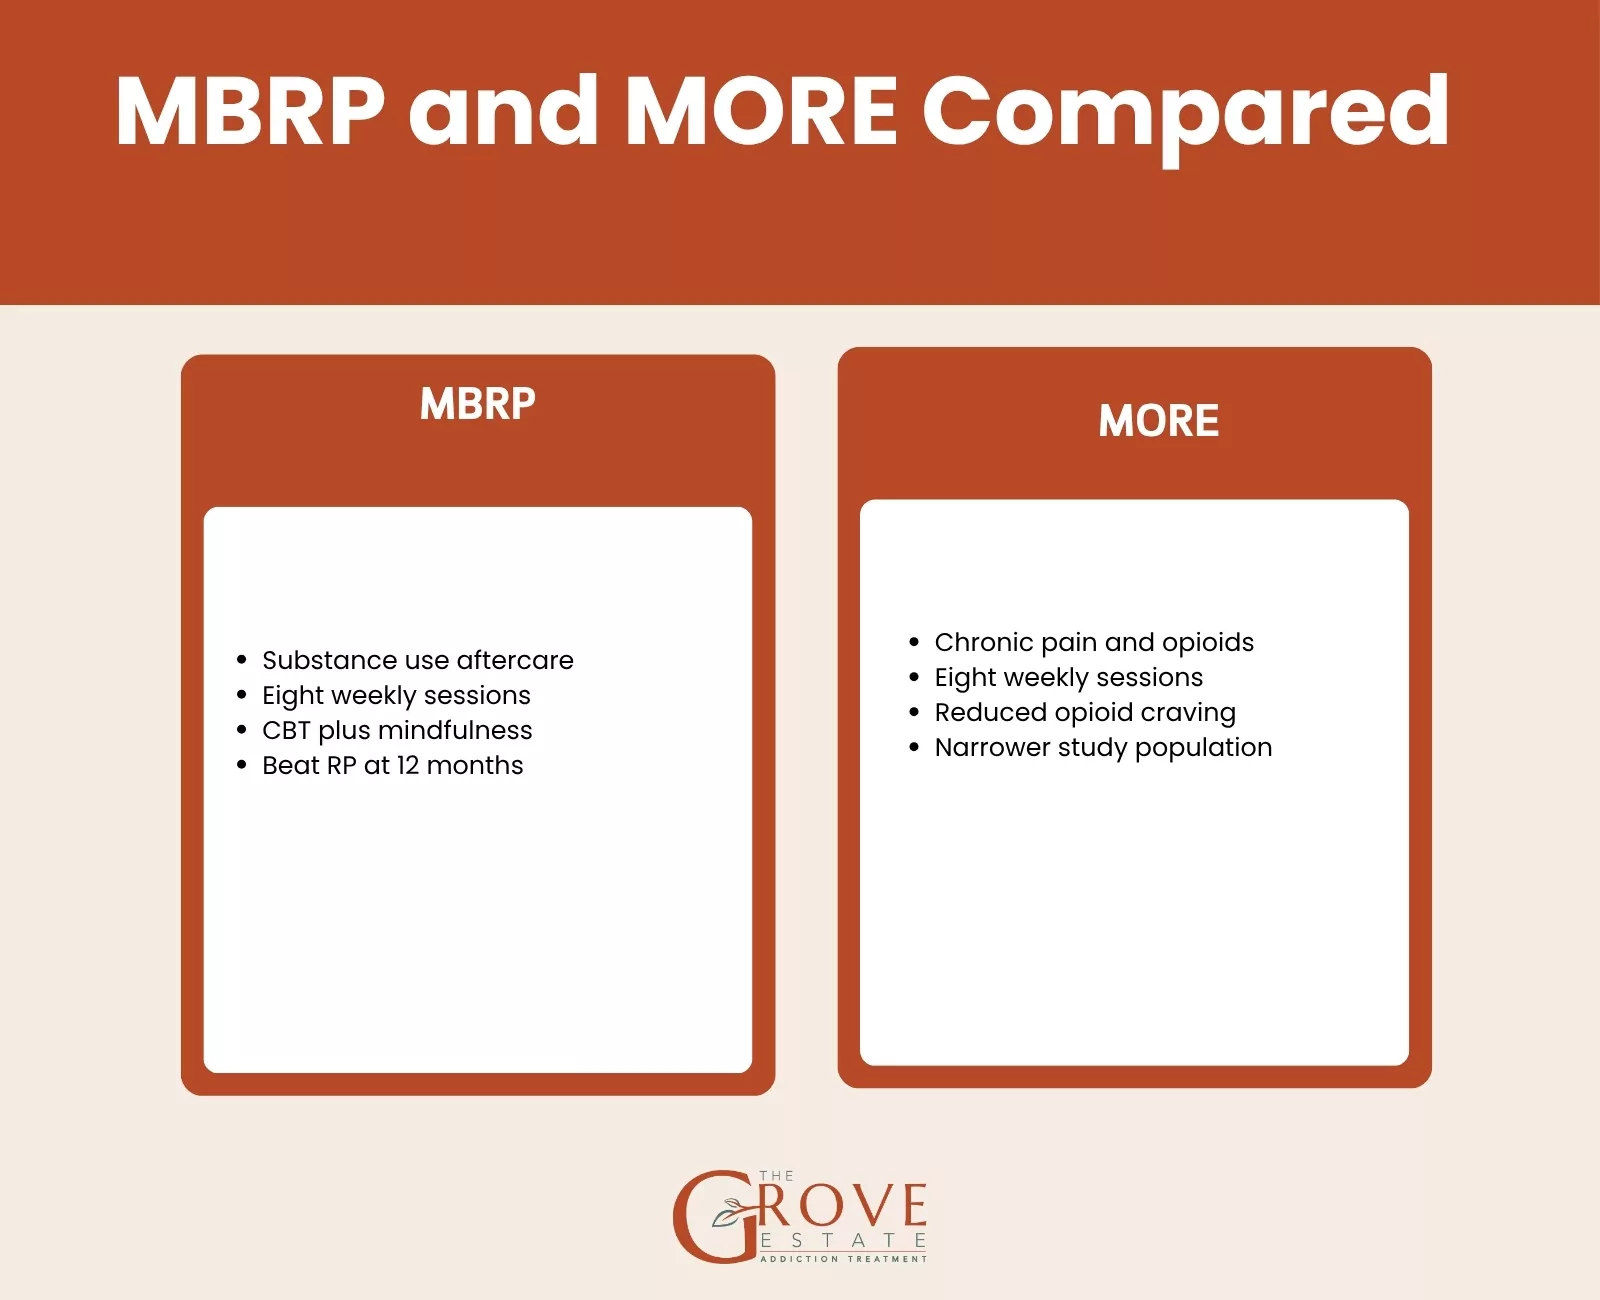
- Mindfulness-Based Relapse Prevention is the addiction-specific protocol. Sarah Bowen, Neha Chawla and G. Alan Marlatt built MBRP as an eight-week outpatient aftercare course combining cognitive behavioral skills with mindfulness practice.
- Its trial evidence favors it at twelve months: A randomized clinical trial found MBRP produced significantly less drug use and a lower probability of heavy drinking than standard relapse prevention at twelve-month follow-up.
- Eric Garland developed a second protocol: Mindfulness-Oriented Recovery Enhancement runs eight weeks and has been studied mainly in people with chronic pain and prescription opioid misuse.
- The mechanism is response, not relaxation: The aim is noticing a trigger and choosing a response, so a session that feels uncomfortable is not a session that failed.
- Marlatt sits behind two approaches in this cluster: He co-developed MBRP and also shaped harm reduction, which is why the two bodies of work overlap.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Is Mindfulness in Addiction Recovery?
Mindfulness describes deliberate, non-judgmental attention to present experience, applied here to cravings, triggers, and the gap between urge and action.
What It Is Not
Several misunderstandings make the practice harder than it needs to be.
- Not relaxation: The goal is clear attention rather than calm, and calm is a frequent side effect rather than the objective.
- Not emptying the mind: Thoughts continue, and noticing that they have wandered is the practice working rather than failing.
- Not religious practice: The clinical protocols are secular, whatever the historical origins of the techniques.
- Not a substitute for medical care: Physical dependence still requires withdrawal management, because alcohol withdrawal carries seizure risk.
The Three Named Protocols
Three programs matter here, and they descend from one another.
- Mindfulness-Based Stress Reduction: Jon Kabat-Zinn developed MBSR as the parent eight-week course, designed for stress and chronic illness rather than addiction.
- Mindfulness-Based Relapse Prevention: Bowen, Chawla and Marlatt adapted the format specifically for substance use aftercare.
- Mindfulness-Oriented Recovery Enhancement: Garland built MORE to target chronic pain and opioid misuse together.
- They are courses, not techniques: Each runs roughly eight weekly group sessions with daily home practice between them.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
How MBRP Works
MBRP was designed as an eight-week manualized outpatient aftercare program for people who have recently completed more intensive treatment.
The Structure
The course combines two established approaches rather than replacing either.
- Cognitive behavioral skills: Trigger identification and coping planning come from standard relapse prevention.
- Mindfulness practice: Formal meditation and brief informal practices build the capacity to observe an urge.
- Aftercare positioning: The pilot trial enrolled adults who had just finished intensive inpatient or outpatient treatment, so it follows residential care rather than replacing it.
- Home practice matters: Between-session practice is part of the protocol, not an optional extra.
- The target is flexible responding: The stated aim is increased awareness and flexible response in the presence of triggers.
Mindfulness Techniques for Cravings
These are the practices the protocols actually teach, described plainly.

Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!The Core Practices
Each addresses a different moment in the craving cycle.
- Urge surfing: Observing a craving rise, peak, and fall without acting, on the basis that urges are time-limited.
- The breathing space: A brief three-part pause used at the moment of difficulty rather than as a scheduled practice.
- Body scanning: Moving attention through the body to notice where tension and craving register physically.
- Labeling: Naming what is happening, such as noting craving or noting anger, which creates distance from it.
- Mindful movement: Walking or stretching with attention on sensation, useful for people who find seated practice difficult.
- Trigger mapping: Identifying the situations that precede urges, which connects the practice to relapse prevention planning.
Why Urge Surfing Is the Central One
The technique addresses the specific belief that makes cravings dangerous.
- It treats the urge as weather: A craving is framed as a passing event rather than a command.
- It removes the all-or-nothing frame: Waiting out an urge is an available third option between resisting and using.
- It is practiced before it is needed: The skill is rehearsed in low-stakes moments so it exists in high-stakes ones.
What Happens in a Session
Sessions follow a predictable shape across all three protocols.
- Group format: Weekly sessions run in a group with a trained facilitator.
- Guided practice: Each session includes practice done together rather than only discussion of it.
- Review of home practice: What happened between sessions is examined, including the weeks it did not happen.
- A theme per week: The course moves through topics such as automatic pilot, triggers, and self-care in sequence.
Rediscover Life at The Grove Estate
Get the compassionate mental health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our Facility
What the Evidence Shows
The trial evidence is specific, and its limits are as informative as its findings.
MBRP Findings
Two trials carry most of the weight.
- The pilot trial: An eight-week MBRP course was compared with treatment as usual in 168 adults who had recently completed intensive treatment.
- The larger randomized trial: Both MBRP and standard relapse prevention produced significantly lower relapse risk than treatment as usual.
- The twelve-month difference: MBRP produced significantly less drug use and a lower probability of heavy drinking than standard relapse prevention at twelve-month follow-up.
- What that suggests: The advantage appeared over time rather than immediately, which fits a skill that strengthens with practice.
MORE Findings, and Their Scope
Garland’s protocol has a substantial evidence base in a narrower population.
- The studied population: Trials have focused on people with chronic pain and prescription opioid misuse rather than substance use disorders generally.
- Craving outcomes: A stage one randomized trial found MORE reduced moment-to-moment opioid craving and increased self-control over it.
- Opioid dosing: Trial findings included reduced opioid dose among people prescribed opioid analgesics.
- Pooled evidence: A multilevel meta-analysis of randomized trials examined MORE across addictive behavior, psychiatric distress, and chronic pain.
- The honest caveat: Generalizing MORE beyond pain and opioid populations goes further than the trials support.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Mindfulness Does Not Do
Setting expectations accurately protects people from reading ordinary difficulty as failure.
- It does not remove cravings: The practice changes the response to an urge rather than preventing the urge.
- It is not a standalone treatment: MBRP was built as aftercare following intensive treatment, not as a replacement for it.
- It does not manage withdrawal: Physical dependence needs medical supervision, and alcohol withdrawal can escalate to seizures.
- It can surface difficult material: Sustained attention sometimes brings up trauma or grief, which is a reason to practice with a facilitator rather than alone.
- Practice is the hard part: The techniques are easy to understand and difficult to maintain, which is what the eight-week structure exists to address.
Who It Suits, and Who It Does Not
Fit varies, and knowing that in advance prevents a wasted attempt.
- Good fit after intensive treatment: The protocols were designed for the aftercare window, following the levels of addiction treatment.
- Good fit alongside other support: The practice sits comfortably with 12-step participation and with medication.
- Poor fit during acute withdrawal: Attention training is not available to someone who is physically unwell.
- Needs care with untreated trauma: Co-occurring conditions should be addressed alongside rather than after.
Getting Help
Free confidential help is available at any hour, and no diagnosis is needed to call.
- Immediate danger: Call 911 if someone cannot be woken, is breathing irregularly, or is having a seizure.
- Suicide and crisis: Call or text 988 to reach the Suicide and Crisis Lifeline, which operates 24 hours a day.
- Treatment referral: The SAMHSA National Helpline gives free, confidential referral at 1-800-662-4357.
- Finding a course: MBRP and MBSR courses are delivered by trained facilitators, and a treatment provider can refer.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
Wellness Programming at The Grove Estate
The Grove Estate provides wellness programming within residential care on a 25 acre estate in Peru, Miami County, Indiana.

What the Program Provides
The facility holds a single designated level of care.
- ASAM Level 3.5 residential: Clinically Managed High-Intensity Residential care for voluntary adults aged 18 and older.
- Wellness programs: Programming spans full workout programs through relaxation techniques.
- Recreational therapy: Expressive modalities form part of the schedule.
- Counseling and seminars: Individual counseling, group counseling, alcohol and drug seminars, and a family program run at a 12:1 client-to-staff ratio.
- Accreditation: The Joint Commission lists the organization under Health Care Organization ID 696218, and Indiana FSSA DMHA under reference number 2145-010.
What the Program Does Not Include
Stating the boundary prevents anyone arriving expecting a service the facility does not hold.
- Not an MBRP or MORE provider: The facility does not deliver Mindfulness-Based Relapse Prevention or Mindfulness-Oriented Recovery Enhancement as manualized protocols.
- Relaxation is not mindfulness therapy: Wellness programming includes relaxation techniques, which is a different thing from an eight-week mindfulness course.
- One level of care only: The facility holds ASAM Level 3.5 with no partial hospitalization, intensive outpatient, or standalone outpatient designation.
- Aftercare by referral: Because these protocols are outpatient aftercare, discharge planning is where they belong rather than during a residential stay.
Are you covered for treatment?
The Grove Estate is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Frequently Asked Questions
How do you break addictive habits?
The mindfulness approach targets the gap between trigger and action. Urge surfing trains a person to observe a craving rise and fall without acting, on the basis that urges are time-limited. It works best as a rehearsed skill rather than something attempted first during a crisis.
What is mindfulness-based relapse prevention?
An eight-week manualized outpatient aftercare course developed by Sarah Bowen, Neha Chawla and G. Alan Marlatt. It combines cognitive behavioral relapse prevention skills with mindfulness practice, aiming to increase awareness and flexible responding when triggers appear.
Rediscover Life at The Grove Estate
Get the compassionate mental health support you deserve. We're here to help you reclaim joy, wellness, and a brighter future.
Our FacilityDoes mindfulness actually help with addiction?
A randomized clinical trial found MBRP produced significantly less drug use and a lower probability of heavy drinking than standard relapse prevention at twelve-month follow-up, with both outperforming treatment as usual. The advantage emerged over time rather than immediately.
What is urge surfing?
Observing a craving rise, peak and subside without acting on it. The technique reframes an urge as a passing event rather than a command, and provides a third option between resisting and using. It is practiced in low-stakes moments so it is available in harder ones.
How is MORE different from MBRP?
Both run eight weeks. MBRP was designed for substance use aftercare generally. Eric Garland’s MORE targets chronic pain and prescription opioid misuse together, and its trials have focused on that population, so its findings do not automatically transfer to other substances.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
Do I have to meditate for a long time?
No. The protocols include brief practices such as a short breathing space used at the moment of difficulty, alongside longer formal sessions. Consistency matters more than duration, which is why home practice is built into the course structure.
Can mindfulness replace rehab?
No. MBRP was built as aftercare for people who had recently completed intensive inpatient or outpatient treatment. It also cannot manage withdrawal, which needs medical supervision because alcohol withdrawal carries seizure risk.
What if sitting still makes me feel worse?
That is common and worth naming. Sustained attention can surface trauma or grief, which is a reason to practice with a trained facilitator rather than alone. Mindful movement suits people who find seated practice difficult.
Contact us today to schedule an initial assessment or to learn more about our services. Whether you are seeking rehab treatment or simply need guidance on your recovery journey, we are here to help.
References
- Bowen, S., Chawla, N., Collins, S. E., Witkiewitz, K., Hsu, S., Grow, J., Clifasefi, S., Garner, M., Douglass, A., Larimer, M. E., & Marlatt, A. (2009). Mindfulness-based relapse prevention for substance use disorders: A pilot efficacy trial. Substance Abuse, 30(4), 295-305. PMID 19904665.
- Bowen, S., Witkiewitz, K., Clifasefi, S. L., Grow, J., Chawla, N., Hsu, S. H., Carroll, H. A., Harrop, E., Collins, S. E., Lustyk, M. K., & Larimer, M. E. (2014). Relative efficacy of mindfulness-based relapse prevention, standard relapse prevention, and treatment as usual for substance use disorders: A randomized clinical trial. JAMA Psychiatry, 71(5), 547-556. PMID 24647726.
- Garland, E. L., et al. (2022). Mindfulness-Oriented Recovery Enhancement for addictive behavior, psychiatric distress, and chronic pain: A multilevel meta-analysis of randomized controlled trials. PMID 36124231.
- Garland, E. L., Manusov, E. G., Froeliger, B., Kelly, A., Williams, J. M., & Howard, M. O. (2014). Mindfulness-oriented recovery enhancement for chronic pain and prescription opioid misuse: Results from an early-stage randomized controlled trial. Journal of Consulting and Clinical Psychology, 82(3), 448-459. PMID 24491075.
- Garland, E. L. (2018). Mindfulness-based treatment of addiction: Current state of the field and envisioning the next wave of research. Addiction Science & Clinical Practice.
- Comparing the efficacy of mindfulness-based relapse prevention versus relapse prevention for alcohol use disorder: A randomized control trial. PMC10488314
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Association Publishing.
- Substance Abuse and Mental Health Services Administration. (2025). Key substance use and mental health indicators in the United States: Results from the 2024 National Survey on Drug Use and Health (PEP25-07-007). U.S. Department of Health and Human Services.
Share This Post

The Grove Editorial Team
All author posts
ADDICTION TREATMENTS IN INDIANA
Are you covered for treatment?








The Grove Estate is an approved provider for Blue Shield of California and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!

